Understanding Breast Cancer Screening Guidelines: What Changed and Why It Matters
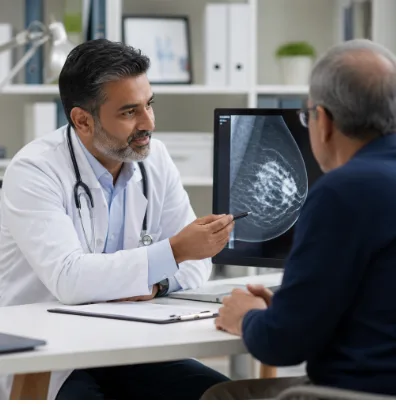
Recent updates to breast cancer screening recommendations have shifted the landscape for millions of women, particularly those in their 40s. The American Cancer Society and other major health organizations now recommend that women at average risk begin annual mammography screening at age 40 rather than 50. This change reflects evolving research on breast cancer incidence, improved imaging technology, and a more nuanced understanding of risk factors that extend beyond age alone.
The implications of these guideline changes extend far beyond scheduling an earlier appointment. They affect insurance coverage decisions, clinical workflow in healthcare facilities, and most importantly, the early detection rates that can dramatically improve treatment outcomes. For women navigating these recommendations, understanding what drove these changes and how they apply to individual circumstances becomes essential to making informed decisions about personal health.
Why Screening Ages Were Lowered
The decision to recommend screening starting at 40 stems from several converging factors. Breast cancer incidence in women aged 40 to 49 has risen over the past two decades, with approximately 12 percent of new diagnoses occurring in this age group. While the absolute risk remains lower than in older populations, cancers detected in younger women often progress more aggressively and may require more intensive treatment approaches.
Mortality data also influenced the shift. Studies demonstrate that regular mammography screening in the 40-49 age group reduces breast cancer deaths by approximately 15 to 20 percent. Though this benefit is smaller than the 30 to 40 percent reduction seen in women over 50, it represents hundreds of lives saved annually when applied across populations. The trade-off between potential harms—including false positives and overdiagnosis—and mortality reduction has tilted toward earlier screening as imaging quality has improved and unnecessary biopsies have declined.
Technology advancements have made screening more effective for younger women, who typically have denser breast tissue that can obscure tumors on traditional mammograms. Digital breast tomosynthesis, commonly called 3D mammography, creates layered images that better distinguish normal tissue from abnormalities. This technology has reduced callback rates while increasing cancer detection rates, addressing one of the primary concerns about screening younger populations.
The Dense Breast Tissue Factor
Breast density presents a dual challenge: it reduces mammography sensitivity and independently increases cancer risk. Dense tissue appears white on mammograms, as do tumors, making detection more difficult. Women with extremely dense breasts face a four to six times higher risk of breast cancer compared to those with mostly fatty breast tissue. This relationship holds true regardless of age, though breast density typically decreases after menopause.
Many jurisdictions now require radiologists to inform patients about their breast density classification, categorized into four groups from almost entirely fatty to extremely dense. New screening protocols increasingly account for density status, with supplemental imaging options like ultrasound or MRI recommended for women in the higher density categories. These additional tests can detect cancers that mammography alone would miss, though they also carry higher false-positive rates and costs.
The conversation about density has moved beyond simple notification. Clinical guidelines now suggest that screening strategies should be individualized based on density combined with other risk factors such as family history, genetic mutations, and prior breast biopsies. This personalized approach represents a departure from one-size-fits-all age-based recommendations toward risk-stratified screening that allocates resources based on likelihood of benefit.
High-Risk Populations and Enhanced Screening
Women with elevated breast cancer risk require screening protocols that differ substantially from average-risk guidelines. Those who carry BRCA1 or BRCA2 gene mutations face a 50 to 85 percent lifetime risk of developing breast cancer, compared to the 13 percent baseline risk for the general population. For these individuals, screening typically begins at age 25 or 10 years younger than the earliest diagnosis in the family, whichever comes first.
High-risk screening usually incorporates breast MRI alternating with mammography at six-month intervals, providing more frequent surveillance with different imaging modalities. MRI demonstrates superior sensitivity for detecting cancers in dense tissue and identifying tumors at earlier stages, though specificity remains lower than mammography, resulting in more benign findings requiring follow-up. The combination approach leverages the strengths of each modality while managing their respective limitations.
Family history assessment has become more sophisticated, moving beyond simple yes-or-no questions about breast cancer in relatives. Detailed pedigree analysis considers the age at diagnosis, bilateral disease, male breast cancer, and associated cancers like ovarian or pancreatic cancer. Risk assessment tools like the Tyrer-Cuzick model calculate lifetime risk percentages that guide whether enhanced screening or risk-reduction strategies make sense for individual patients.
Access to Specialized Breast Care Services
Implementing updated screening guidelines requires infrastructure that extends beyond imaging equipment. Comprehensive breast programs integrate radiologists, surgeons, medical oncologists, genetic counselors, and reconstruction specialists within coordinated care pathways. This multidisciplinary approach ensures that abnormal findings move quickly through diagnostic workup and, when needed, into treatment planning without patients navigating disconnected healthcare silos.
For women in Abu Dhabi seeking this level of coordinated care, programs that bring together screening, diagnosis, and treatment planning under one umbrella offer significant advantages. Consulting an oncologist abu dhabi who works within a multidisciplinary breast health team means access to genetic testing for high-risk assessment, advanced imaging including MRI and molecular breast imaging, targeted therapies and immunotherapy options, and breast reconstruction services including microsurgical techniques. This integrated model reduces delays between detection and treatment initiation, which can meaningfully impact outcomes particularly for aggressive cancer subtypes.
Geographic access to specialized services matters considerably. Rural and underserved populations often face substantial barriers to implementing screening recommendations, with limited access to 3D mammography, long travel distances to biopsy facilities, and delayed appointments with specialists. Mobile mammography programs and telemedicine consultations have partially addressed these disparities, though gaps remain particularly for follow-up procedures that require in-person visits.
Making Informed Screening Decisions
Translating population-level guidelines into personal screening plans requires honest conversations about individual risk factors, screening test characteristics, and personal values regarding uncertainty and intervention. Understanding screening test accuracy, including sensitivity and specificity rates, helps set realistic expectations about what mammography can and cannot detect.
The conversation should include false-positive rates, which range from 7 to 12 percent per screening round, meaning that over 10 years of annual screening, approximately 50 to 60 percent of women will experience at least one callback for additional imaging. Most of these resolve without biopsy, but the anxiety and additional procedures represent real costs that women balance against mortality reduction benefits. Shared decision-making frameworks help patients weigh these trade-offs based on their risk tolerance and life circumstances.
Insurance coverage for enhanced screening modalities varies significantly. While screening mammography is universally covered under preventive care mandates in many countries, supplemental imaging like breast MRI or molecular breast imaging may require documentation of high-risk status. Understanding coverage policies before scheduling supplemental tests prevents unexpected financial burdens and allows for informed decisions about out-of-pocket expenditures.
Beyond Screening: Risk Reduction Strategies
While screening detects existing cancers earlier, risk reduction strategies aim to prevent cancer development altogether. Lifestyle modifications offer modest but measurable benefit: maintaining healthy body weight, limiting alcohol consumption to fewer than three drinks per week, regular physical activity, and breastfeeding for those who have children all correlate with reduced breast cancer incidence.
For women at substantially elevated risk, medical interventions provide more dramatic risk reduction. Chemoprevention with selective estrogen receptor modulators like tamoxifen reduces breast cancer incidence by approximately 50 percent in high-risk premenopausal women, though side effects including menopausal symptoms and thromboembolic risk require careful consideration. Aromatase inhibitors offer similar benefits for postmenopausal women with different side effect profiles, primarily affecting bone density and joint symptoms.
Prophylactic mastectomy remains the most effective risk reduction strategy for women with BRCA mutations or other high genetic risk, reducing breast cancer incidence by more than 90 percent. However, this irreversible surgical intervention carries significant physical and psychological implications. The decision involves careful consideration of timing, reconstruction options, and personal values around risk tolerance and quality of life.
Looking Forward
Breast cancer screening continues evolving as artificial intelligence tools enter clinical practice, potentially improving detection accuracy and reducing radiologist workload. Risk prediction models incorporating polygenic risk scores from genetic testing may further refine screening recommendations, moving toward truly personalized schedules based on individual cancer probability rather than age-based cutoffs.
The shift toward earlier screening represents current best evidence for reducing breast cancer mortality, but it requires healthcare systems to expand capacity and women to engage actively with their breast health. Understanding the rationale behind guideline changes, knowing personal risk factors, and accessing coordinated care services when needed all contribute to translating screening recommendations into meaningful health outcomes.